
Patient safety

How do you dispose unused medications?

What should you do with expired medicines, leftover tablets or unused syrups? Should they go into the dustbin, down the sink or back to a pharmacy?

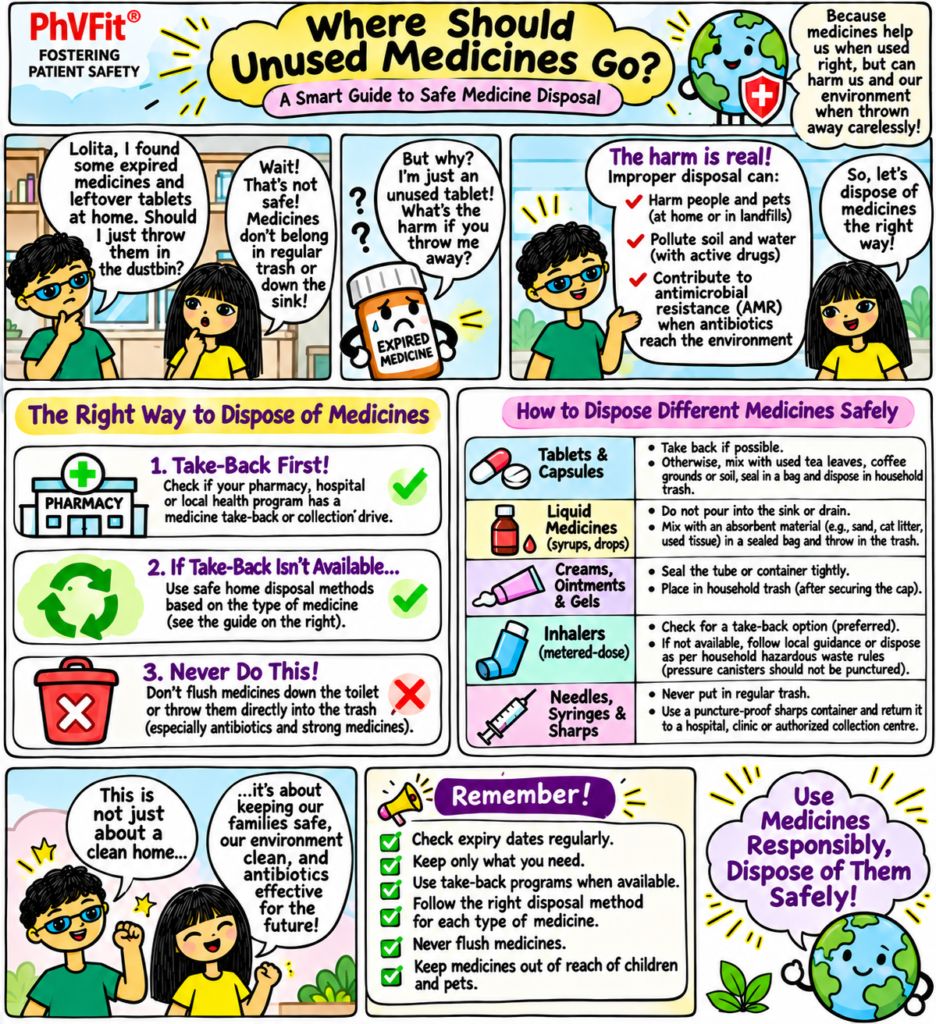
The PhVFit Safe Medicine Disposal Comic Strip uses an engaging conversation between Arjun and Lolita to help school students understand the importance of disposing of medicines safely and responsibly.
What does this comic teach?

  • Medicine take-back programmes: Why returning unused or expired medicines to pharmacies, hospitals or authorised collection centres is generally the preferred option where available.
  • Safe disposal of tablets and capsules: Understanding why medicines should not be discarded carelessly and why local disposal guidance matters.
  • Liquid medicines, syrups and drops: Learning why medicines should not simply be poured into sinks or drains.
  • Creams, ointments and gels: Understanding the importance of securing medicine containers before disposal.
  • Inhalers: Recognising that inhalers may require special handling and should be disposed of according to local guidance.
  • Needles, syringes and sharps: Learning why these must never be thrown into ordinary household waste and should be placed in appropriate sharps containers.
  • Protecting people and the environment: Understanding how irresponsible disposal can expose people and animals to medicines and contribute to environmental contamination.

A classroom resource for medication safety education

Designed as part of the PhVFit School Medication Safety Toolkit, this one-page comic can be used by teachers, schools, healthcare professionals and NGOs to introduce safe medicine disposal through storytelling.

Students can read the comic, discuss everyday situations involving unused medicines and learn practical ways to protect their families, communities and environment.

Its simple, visual format makes it suitable for classroom discussions, school health awareness programmes and medication safety campaigns.

The message is simple: Medicines need responsible use—and responsible disposal too!

PhVFit | Fostering Patient Safety
Patient safety research – how important?

If you are working on oncology studies, have you noticed that complete radical mastectomy is usually reported pre-1980 for breast cancer patients. Have you thought about the reason?

Radical mastectomy used to be a norm in America after Halsted first established the procedure in 1894. This Surgery entailed removal of breast, chest muscles, and all of the lymph nodes under the arm, and this was thought to be the only option to treat breast cancer. Halsted based his surgery on centrifugal theory. In Emperor of all maladies, Siddhartha Mukherjee explains this as – cancer like a malevolent pinwheel, tended to spread in ever-growing arcs from a single central focus in the body. A surgeon’s job was to arrest the centrifugal speed by cutting every piece of it out of the body, as if to catch and break the wheel in midspin. The more a surgeon cut, the more it cured. However, morbidity after the operation was great, because the large wounds were left to heal by granulation, lymphedema was near universal, and arm movement was severely restricted (due to pectoralis muscle removal and damage to axilla nerves). For these reasons, chronic pain was also an important sequela. 

Another oncologist Geofferey Keynes was not so convinced about Halsted’s theory. 1n 1924, from experience with his patients, he saw that a lumpectomy, a much less invasive procedure along with radiation, worked just as well but with much less morbidity. The relapse rates were almost equal as with Radical mastectomy but the quality of life for the patients was much better. He presented his data but his ideas were not taken seriously as the surgeons of that time were completely sold to the centrifugal theory. 

In 1953 (almost 30 years later), George Crile, a follower of Halsted theory started having his doubts about radical mastectomy. His research and studies revealed that the cancer spread was more erratic and unpredictable. The patients treated with radical mastectomy also relapsed and died due to metastasis. He came to understand that either the breast cancer is a highly localised disease – thus curable by a smaller mastectomy – or an inherently systemic disease – thus uncurable event by the most exhaustive surgery. He gave up radical mastectomy altogether and started following the Keynes’s procedure and saw that the survival rate of patients in the two surgeries had no difference. Separated by 40 years of clinical practice, both Keynes and Crile had seemingly stumbled on the same clinical truth.

However, it took another twenty years, and dedicated efforts and clinical trials by another great oncologist Bernard Fisher to establish the futility and danger of a complete radical mastectomy. It will also be interesting to note that the withdrawal of radical mastectomy was also sped up due to the thalidomide disaster in 1960s. Fallibilities in the medical discipline surfaced and patients recognized that one of the most common and disfiguring operations was never tested in a trial, women refused radical mastectomies. Clinical trials were conducted by Fisher to prove his findings! However, they were not without obstacles. It took him around 10 years to gather all data.

Meanwhile, more mutilating and invasive procedures liked extended radical mastectomy were also tried and abandoned due to high mortality rates! 

A radical mastectomy is rarely performed now and has been replaced by less invasive procedures. I wonder if medical fraternity at that time was more accepting of the new ideas and theories, would it have taken as much as almost a century to reach this decision?