One Safety Concern, Different Regulatory Responses: The Ferric Carboxymaltose Story

One safety concern. Multiple regulatory responses. One important question for global pharmacovigilance: what should happen next in every market where these products are authorised?

The third quarter of 2026 has brought an important pharmacovigilance development around ferric carboxymaltose (FCM) and the risk of hypophosphataemia.

On 1 September 2026, the US FDA required a boxed warning for ferric carboxymaltose injection concerning symptomatic hypophosphataemia. The FDA’s assessment used multiple evidence sources, including its adverse-event database, published literature and the Sentinel System. FDA also found that serum phosphate testing occurred in fewer than 20% of ferric carboxymaltose administration episodes in the Sentinel data reviewed.

Only days later, EMA’s Pharmacovigilance Risk Assessment Committee initiated a review of injectable iron-containing medicines. The review is examining hypophosphataemia and related bone complications, including osteomalacia, as well as the effectiveness of existing risk-minimisation measures.

This makes the story bigger than a label change.

It raises a fundamental pharmacovigilance question:

If a safety risk is already known, but the risk-minimisation measure may not be producing the intended behaviour in clinical practice, what should regulators and MAHs do next?

What happened?

FDA: From warning to boxed warning

The FDA has strengthened the US prescribing information for ferric carboxymaltose to highlight the risk of symptomatic hypophosphataemia.

This is not a newly identified adverse reaction.

FDA had previously strengthened the Injectafer label:

  • 2020: warning added concerning serious symptomatic hypophosphataemia
  • 2023: phosphate-monitoring recommendations added for patients at risk and those receiving repeat treatment within three months
  • 2025: additional risk factors were added
  • 2026: FDA escalated the warning to a boxed warning following a further assessment using FAERS/AEMS, literature and Sentinel data.

The regulatory question has therefore evolved from:

“Is there a risk?”

to:

“Are existing measures sufficiently effective to control the risk?”

EMA: Looking beyond one product

EMA’s PRAC has initiated an EU-wide review of parenteral iron-containing medicines.

The review includes ferric carboxymaltose, ferric derisomaltose, iron dextran, ferric gluconate, ferric hydroxide polymaltose complex and iron sucrose.

Importantly, EMA is not assuming that all injectable iron products have identical risk profiles.

Rather, it is assessing whether the available evidence warrants regulatory changes across the relevant products.

The review was triggered by serious cases, including cases of osteomalacia, and reports of hypophosphataemia after only one or two FCM doses, including in patients without recognised risk factors. EMA also identified potential delays in diagnosis because symptoms such as fatigue, muscle pain and bone pain can overlap with iron-deficiency symptoms.

EMA’s referral documentation reports  793 suspected post-marketing cases involving hypophosphataemia-related terms between January 2023 and June 2026; 81% were classified as serious. The analysis identified that 767 involved hypophosphatemia with only one suspected medicinal product. The data indicate that clinically significant hypophosphatemia can occur even after one or two doses or limited exposure, contradicting the current focus on long term and high dose treatment.

International Regulatory Response

UK MHRA: Risk already recognised and reinforced

The UK has been communicating the risk of symptomatic hypophosphataemia with ferric carboxymaltose for several years.

The MHRA advises monitoring serum phosphate in patients:

  • receiving multiple higher-dose administrations
  • receiving long-term treatment
  • with pre-existing risk factors such as vitamin-D deficiency, malabsorption, secondary hyperparathyroidism, inflammatory bowel disease or osteoporosis.

Healthcare professionals are also advised to reconsider treatment where hypophosphataemia persists.

Importantly, a September 2026 post-publication note clarifies that the risks described in the MHRA communication apply to all ferric carboxymaltose products, not only the originally referenced Ferinject brand.

The UK example illustrates that regulatory action does not necessarily begin with a new warning.

It can involve clarifying the scope and applicability of an existing safety measure across products containing the same active substance.

Australia TGA: Earlier action and continued monitoring

Australia’s TGA has previously recognised symptomatic hypophosphataemia as a known risk with ferric carboxymaltose.

TGA advised healthcare professionals to evaluate patient risk factors before treatment and follow up patients considered at risk. Its safety review also highlighted the possibility that persistent fatigue, weakness or other symptoms could be incorrectly attributed to continuing iron-deficiency anaemia rather than hypophosphataemia.

TGA’s earlier pharmacovigilance review identified reports of hypophosphataemia with ferric carboxymaltose, including severe cases and skeletal manifestations.

The Australian experience demonstrates the value of longitudinal safety surveillance: a known risk can remain clinically important even when it has already been reflected in product information.

Hong Kong: An example of active regulatory intelligence

Hong Kong provides perhaps the most interesting example for this discussion.

Following earlier international safety communications, Hong Kong’s Pharmacy and Poisons Board decided in December 2020 that the sales-pack label and/or package insert for registered ferric carboxymaltose products should include safety information concerning:

  • hypophosphataemia
  • hypophosphataemic osteomalacia
  • serum phosphate monitoring in patients with risk factors
  • monitoring in patients receiving multiple higher-dose administrations or long-term treatment.

Following the FDA’s September 2026 boxed warning, Hong Kong’s Department of Health issued another safety communication.

It reported that Hong Kong had two registered ferric carboxymaltose products and that, at that time, it had received one ADR report involving ferric carboxymaltose, although that case was not related to hypophosphataemia.

More importantly, Hong Kong stated that it would remain vigilant regarding the outcome of the EMA review and safety updates from other regulatory authorities and consider whether further local action was necessary.

This is the regulatory-intelligence model in action:

International regulatory signal → local assessment → monitor emerging evidence → determine whether local action is warranted.

What does this mean for India?

The recent FDA and EMA developments are also relevant from an Indian regulatory-intelligence perspective.

India has an established pharmacovigilance framework through CDSCO and the Pharmacovigilance Programme of India (PvPI), and Indian regulatory authorities periodically issue safety alerts, label-related directions and other communications in response to emerging safety information.

As of 29 September 2026, we have not identified a publicly available CDSCO or PvPI communication specifically addressing the latest FDA boxed warning for ferric carboxymaltose or the ongoing EMA review of parenteral iron-containing medicines.

This is worth monitoring as the international regulatory assessments evolve.

The absence of a specific public communication at this stage does not necessarily indicate that no assessment is taking place. Regulatory authorities may review emerging evidence through their established pharmacovigilance and regulatory processes before determining whether any local action is warranted.

What should Indian MAHs be watching?

For companies manufacturing or marketing ferric carboxymaltose in India, the international developments provide an important regulatory-intelligence input.

Areas worth reviewing include:

  • the emerging FDA and EMA assessments of hypophosphataemia;
  • the company’s cumulative global and Indian safety data;
  • cases involving severe or symptomatic hypophosphataemia and hypophosphataemic osteomalacia;
  • relevant risk factors and repeat/high-dose exposure;
  • current Indian product information and risk-minimisation measures;
  • the company’s assessment of regulatory actions in other markets; and
  • any implications for ongoing aggregate safety assessment, signal management or benefit-risk evaluation.

The key consideration for a global MAH is not necessarily whether the same regulatory action should be replicated in India, but whether new international evidence changes the company’s assessment of its product in the Indian market.

As the EMA review progresses and other regulators continue to assess the emerging evidence, the regulatory landscape for parenteral iron products may become clearer.

For Indian PV professionals, this is therefore a developing regulatory-intelligence story rather than a concluded regulatory position.

Global Regulatory Perspective: What Does This Mean Across Markets

A regulatory action in one market does not automatically become a regulatory action everywhere.

For a global MAH, however, it is an important regulatory-intelligence signal that warrants assessment across markets.

The ferric carboxymaltose story illustrates this well:

  • FDA has escalated the US warning following continued evidence of clinically significant hypophosphataemia.
  • EMA is undertaking a broader review of parenteral iron medicines and existing risk-minimisation measures.
  • MHRA has existing safety measures and has clarified that the identified risks apply to all ferric carboxymaltose products.
  • TGA has previously issued safety advice concerning hypophosphataemia with ferric carboxymaltose.
  • Hong Kong is monitoring the international regulatory developments and the outcome of the EMA review.
  • PMDA revised precautions for ferric carboxymaltose and saccharated ferric oxide in June 2026.

For India, this is particularly relevant given the country’s position as a major global manufacturer and marketer of medicines, including generic products.

For companies operating across multiple markets, timely awareness of international safety signals and regulatory actions is therefore important for assessing whether emerging evidence has implications for their Indian products, safety data, product information and risk-minimisation measures.

The regulatory response will, of course, depend on the evidence and requirements applicable in each jurisdiction.

The broader regulatory-intelligence lesson is simple:

When one major regulator acts on a safety concern, global MAHs need to understand not only what changed in that market, but whether the underlying evidence has implications for their products and patients elsewhere.
How do you dispose unused medications?

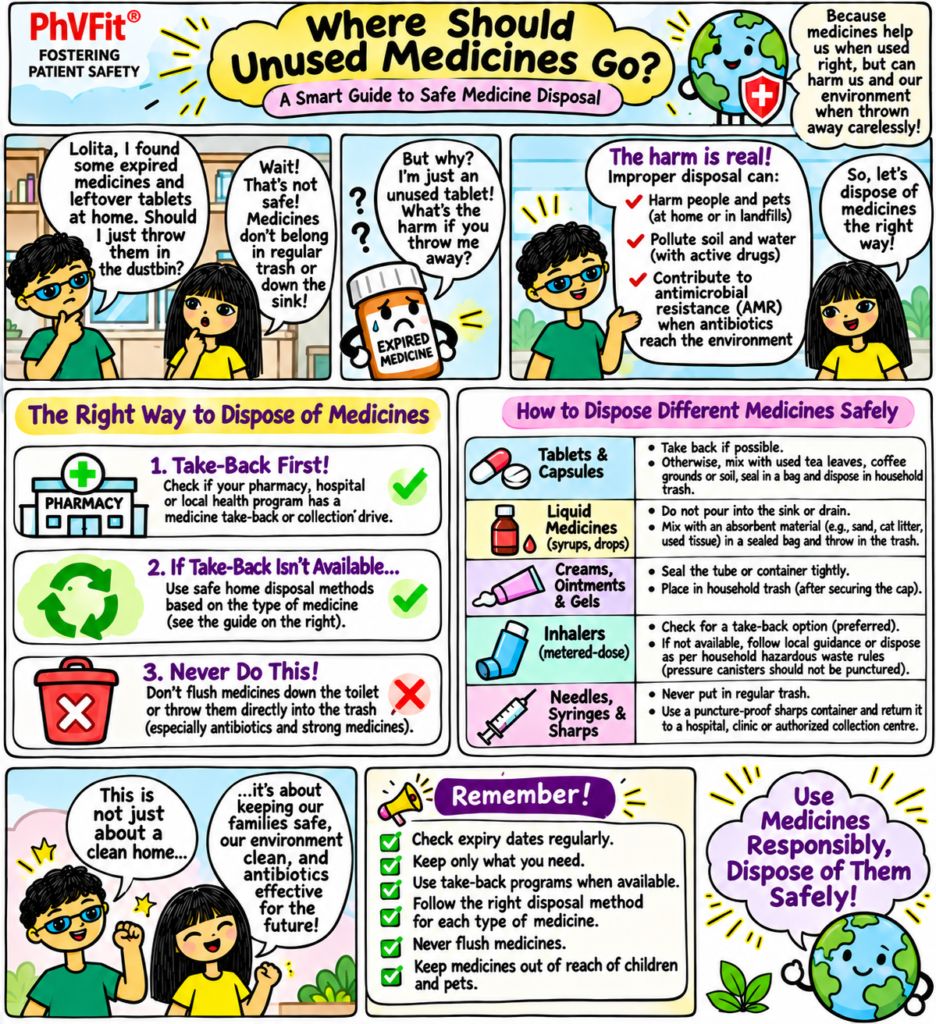
What should you do with expired medicines, leftover tablets or unused syrups? Should they go into the dustbin, down the sink or back to a pharmacy?

The PhVFit Safe Medicine Disposal Comic Strip uses an engaging conversation between Arjun and Lolita to help school students understand the importance of disposing of medicines safely and responsibly.

What does this comic teach?

  • Medicine take-back programmes: Why returning unused or expired medicines to pharmacies, hospitals or authorised collection centres is generally the preferred option where available.
  • Safe disposal of tablets and capsules: Understanding why medicines should not be discarded carelessly and why local disposal guidance matters.
  • Liquid medicines, syrups and drops: Learning why medicines should not simply be poured into sinks or drains.
  • Creams, ointments and gels: Understanding the importance of securing medicine containers before disposal.
  • Inhalers: Recognising that inhalers may require special handling and should be disposed of according to local guidance.
  • Needles, syringes and sharps: Learning why these must never be thrown into ordinary household waste and should be placed in appropriate sharps containers.
  • Protecting people and the environment: Understanding how irresponsible disposal can expose people and animals to medicines and contribute to environmental contamination.

A classroom resource for medication safety education

Designed as part of the PhVFit School Medication Safety Toolkit, this one-page comic can be used by teachers, schools, healthcare professionals and NGOs to introduce safe medicine disposal through storytelling.

Students can read the comic, discuss everyday situations involving unused medicines and learn practical ways to protect their families, communities and environment.

Its simple, visual format makes it suitable for classroom discussions, school health awareness programmes and medication safety campaigns.

The message is simple: Medicines need responsible use—and responsible disposal too!

PhVFit | Fostering Patient Safety

The Safe Medicine Squad: AMR Awareness Comic Strip for School Students | PhVFit Toolkit

Understanding Antimicrobial Resistance (AMR) through storytelling

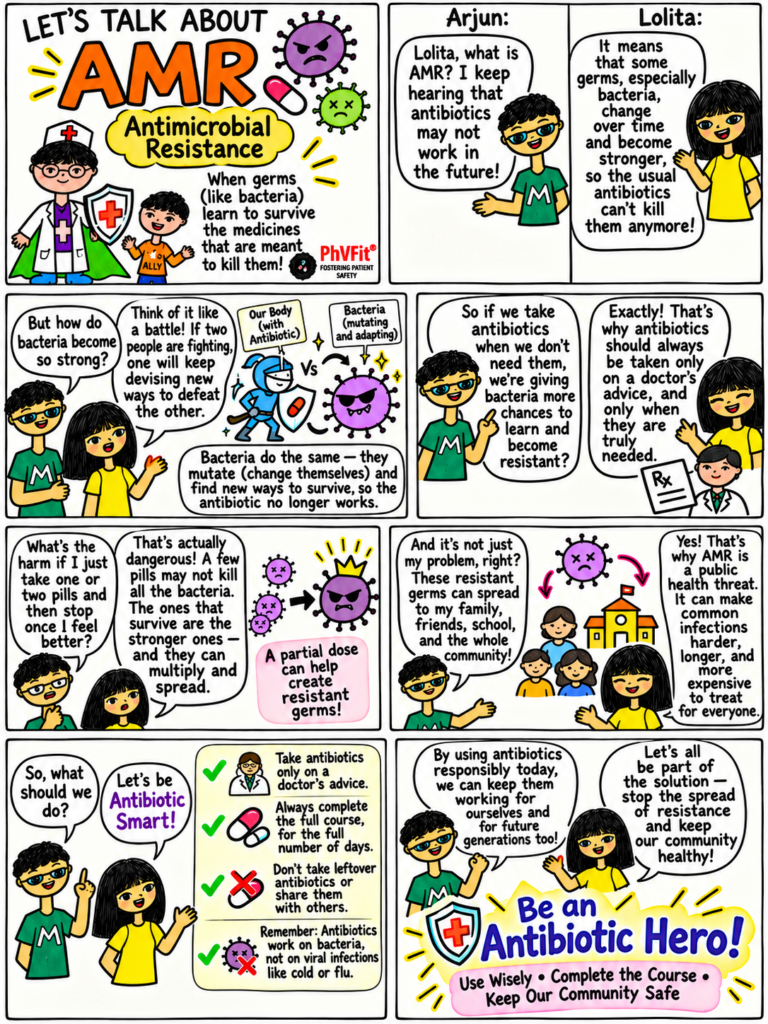
How do we explain antimicrobial resistance to school students in a way they can understand, remember and discuss? The PhVFit AMR Awareness Comic Strip uses a colourful, child-friendly story featuring Arjun and Lolita to introduce students to antimicrobial resistance (AMR), antibiotic resistance and the importance of responsible antibiotic use.

Through simple conversations, relatable examples and engaging illustrations, the comic explains how bacteria can change over time and develop resistance to antibiotics, making these medicines less effective. A simple analogy of two people trying to outsmart each other helps children understand how bacteria adapt and survive when exposed to antibiotics.

The comic also explores why taking antibiotics without a doctor’s advice, stopping treatment prematurely or using leftover antibiotics can contribute to the development and spread of antibiotic resistance. It highlights an important public health message: AMR is not just an individual’s problem. Resistant bacteria can spread through families, schools and communities, making common infections harder to treat.

What will students learn?

  • What is antimicrobial resistance? Understand what AMR means and why antibiotics may stop working against resistant bacteria.
  • How does antibiotic resistance develop? Learn how bacteria can mutate and adapt to survive exposure to antibiotics.
  • Why should antibiotics be taken only on medical advice? Understand the risks of unnecessary and inappropriate antibiotic use.
  • Why follow the prescribed treatment? Learn to take antibiotics exactly as prescribed and for the duration advised by the healthcare professional.
  • Why should antibiotics never be shared? Understand why leftover medicines should not be reused or shared with others.
  • Antibiotics are not for every infection: Learn that antibiotics work against bacteria, not viruses that cause illnesses such as the common cold and flu.
  • AMR is a community concern: Discover how resistant bacteria can spread beyond one individual and affect public health.

How can teachers use this AMR comic strip?

This one-page educational comic can be used as a classroom reading activity, a starting point for group discussions, a school health awareness session or an interactive activity during World AMR Awareness Week.

Teachers can invite students to read the conversations between Arjun and Lolita, discuss the examples, identify unsafe antibiotic-use practices and reflect on how their choices can help protect the wider community.

Its simple one-page format makes it easy to print, share and use as a quick classroom learning resource.

About the PhVFit School Medication Safety Toolkit

The PhVFit School Medication Safety Toolkit aims to build medication awareness and responsible medicine-use habits among children and young people through accessible, engaging and age-appropriate learning resources.

Be Antibiotic Smart. Use antibiotics responsibly. Help protect their effectiveness for everyone.

Resource: PhVFit | Patient Safety and Medication Awareness

When Pharma Builds In-House and Service providers Build Technology

The changing economics of pharmacovigilance services

For years, the life-sciences operating model relied on a network of specialized partners. Pharmaceutical companies retained responsibility for their products, safety oversight and regulatory obligations, while CROs delivered PV operations, technology consultants implemented and supported safety systems, and hosting partners managed the underlying infrastructure.

These roles often overlapped, but their boundaries were relatively distinct. Today, they are becoming less clear.

Pharmaceutical companies are building deeper capabilities through Global Capability Centres (GCCs). CROs are expanding into technology products and platforms. Companies traditionally focused on implementing or hosting established safety databases are developing proprietary solutions, while specialist PV providers are turning domain expertise into products. AI-native entrants are targeting individual workflows with generative AI and automation.

The result is a changing competitive landscape in which services, technology and in-house capabilities increasingly intersect.

GCCs: No longer just delivery centres?

Pharmaceutical companies are expanding GCC capabilities beyond traditional support functions into specialised operations, technology, analytics and innovation.

Novo Nordisk has also established a Bengaluru GCC with broad capabilities spanning pharmacovigilance (manages roughly 75% of global pharmacovigilance caseload), regulatory reporting, clinical data management and other global functions. Sanofi is expanding its Hyderabad GCC, while Eli Lilly is growing its Indian capabilities in AI, automation and software engineering. Bristol Myers Squibb has established a Hyderabad innovation hub focused on drug development and digital capabilities, and Takeda has been exploring expanded GCC capabilities in AI, data science and digital health.

For PV, this could translate into greater in-house ownership of selected safety operations, analytics, system support and automation. This shift may change which activities pharmaceutical companies choose to retain internally and which they continue to source externally.

CROs and specialist PV providers: From services to technology

CROs are increasingly combining operational delivery with proprietary technology and AI. IQVIA’s Vigilance Platform supports safety case management and reporting, while ICON offers tools such as ORCA Safety and Signet for safety monitoring and signal visualisation. PPD combines PV services with its SafetyNet Suite, Syneos Health has developed PV Hub and a generative AI-enabled case-intake solution, and Parexel’s acquisition of Vitrana brought technology capabilities, including HiLIT, into its patient safety portfolio.

Specialist providers are following different paths. Continuum, a life-sciences services company spanning PV, health economics and outcomes research (HEOR), and regulatory affairs, is diversifying into products such as COLMAP for literature management, ARINA for aggregate reporting and COSMAP for signal management. ACI and HAROM have also expanded from PV services and training into technology, including HAROM Safety Vault.

Meanwhile, Nextrove, RxLogix and Ultragenic, which have built capabilities around the implementation, hosting and support of established safety platforms such as Oracle Argus and Veeva, are also developing proprietary PV technology solutions.

These examples illustrate how some PV providers are extending their domain expertise beyond traditional service delivery through proprietary software, specialised applications and technology-enabled workflows.

AI-native entrants: Targeting specific PV workflows

A new category of companies is developing AI-focused tools for individual pharmacovigilance activities. Yeza.ai focuses on AI agents for safety intake, triage and E2B generation; Graph Safety (GraphAI) is developing an AI-oriented patient safety platform; DrugCard applies AI to literature monitoring and regulatory intelligence; and Pivot Path, through its NovaVigil platform, targets workflows including literature monitoring, case intake and signal detection.

Their capabilities and maturity differ, but these examples illustrate how new entrants can target specific PV workflows without necessarily building an entire safety database.

Generative AI: Will it change the economics of building PV products?

Generative AI may make it easier to experiment with specialised tools for ICSR intake, literature screening, quality checks, regulatory intelligence and other PV workflows. Domain experts could potentially collaborate with technology specialists to develop focused solutions without undertaking the same scale of software development traditionally required.

However, lower barriers to experimentation may not automatically translate into lower deployment costs or sustainable business value. A working prototype is very different from a validated, secure and reliable solution operating in a regulated environment.

The real test will be performance in production: how well tools handle real-world safety data, integrate with existing workflows, maintain output quality and scale, and reduce costs after accounting for human review, validation and ongoing maintenance. Adoption will ultimately depend on demonstrable efficiency gains and cost-effectiveness, not projections or successful pilots alone.

A competitive squeeze—or a reshaping of the market?

As GCCs build internal expertise, pharmaceutical companies may retain greater control over selected operations, technology strategy, analytics and automation. External service providers may increasingly be engaged for specialised expertise, complex workloads, implementation support and flexible capacity.

Technology providers could face similar shifts as clients customise established platforms, build internal tools and develop their own automation. Rather than eliminating external vendors, this may change expectations around integration, specialised functionality and the value delivered beyond the software itself.

The future may not be a simple choice between insourcing and outsourcing. Hybrid models could emerge in which GCCs own strategy and critical capabilities, technology partners provide platforms and specialist solutions, and service providers deliver expertise and flexible execution.

In this environment, providers that combine strong PV domain knowledge with technology capabilities may have an advantage. Their ability to translate expertise into integrated solutions could become an important differentiator, provided they can demonstrate measurable value and reliable performance in real-world settings.

For PV service providers, the strategic question is therefore not simply how to compete with increasingly capable clients, but where external expertise can complement internal capabilities most effectively.

Disclaimer: The companies and examples mentioned are illustrative, not exhaustive, and represent a selection of developments across the PV services and technology landscape. Product capabilities and maturity may change over time; specific offerings should be verified with the respective providers.

Perspectives and voices Patient safety May 22

“Voices and Perspectives in Patient safety” 

A PhVFit initiative where we bring to you insights on patient safety from industry and healthcare experts. The insights are conversation starters and food for thought, a joining of hands for a movement in patient safety.  

This Month, we have Dr. Maya Sharma, Global Medical Director, Modi Mundipharma & Win Medicare, sharing her thoughts with us.

Thank you Dr. Maya for sharing your valuable insights with us!

A robust reporting system is the foundation of any pharmacovigilance system, there is a dire need of strengthening the reporting system in India to make Pharmacovigilance an active practice to ensure patient safety. Robust PV systems and PV training across all stakeholders is need of the hour!

Why Pharmacovigilance?

What is the probability of a house catching fire? Very bleak, right.

In the society where my parents live, the lane surrounding the building is narrow. Due to the lack of ample parking area, the extra cars are parked on the lane, which leaves not much space. There was a talk from RWA some time ago on building sheds for that parking space so that people get the covered parking (something builder had promised).

Elders from the society started resisting that move giving the reason that it will become a permanent structure and no big vehicle (e.g. a fire brigade) can then be brought in easily – in case of a fire incident. The team insisting on building sheds did not seem to get the point, whats the probability of a house catching fire, right??

However, the elders kept their foot down and even filed a case to stop this from happening. The project was stalled.

And then it happened! The flat diagonally opposite ours (on the same floor) caught fire. It was an accident and in a matter of half an hour, the fire reached the flats above. The fire extinguishers installed in the society were faulty and were not working. The fire brigade was called. It took some time to remove the cars from there, so that a fire brigade vehicle can enter. It took hours extinguishing the fire and the house was devastated.

Now, imagine, had they built the sheds, how fire brigade would have entered! Yes, fire incidents happen rarely but does that mean we do not plan for them? Risk management, assessment and mitigation is a very important part of any process.

Why am I telling you this story?

The main purpose of pharmacovigilance is also risk mitigation and management. The possibility of an Adverse event happening might be 1 in a million, but the data we collect and assess gives us an understanding on how to manage that risk. Clotting events with vaccines is a rare event, but if a patient unfortunately experiences it, the knowledge can help in early diagnosis and management of the event (when we know the cause) and can save lives! This is the reason, we need a robust reporting and analytics system in Pharmacovigilance, so that risks can be assessed and mitigated.

Are you reporting?

#riskmanagement #pharmacovigilance #pvpi 3Analytics Sushil Jha Dr. Dharani Munirathinam Dr Manoj Swaminathan MBBS, MPH, MRQA amitav banerjee Dr J Vijay Venkatraman Dr. Subhrojyoti Bhowmick, MD

Regulatory authorities for different countries

Global Pharmacovigilance laws and regulations – IAOCR Directory

  • Serbia – Medicines and Medical Devices Agency of Serbia
  • Slovakia – State Institute for Drug Control
  • Slovenia – Ministry of Health
  • Spain – Spanish Medicines Agency
  • Sweden – Medical Products Agency
  • Switzerland – Swiss Agency for Therapeutic Products
  • Ukraine – Ministry of Health
  • United Kingdom – Medicines and Healthcare Regulatory Agency (MHRA)
  • Bahrain – I-SEHA
  • Egypt – Ministry of Health
  • Iran – Ministry of Health
  • Israel – Ministry of Health
  • Jordan – Jordan Food and Drug Administration
  • Lebanon – Ministry of Public Health
  • Saudi Arabia – Saudi Food and Drug Authority
  • United Arab Emirates – Ministry of Health
  • Bangladesh – Directorate General of Drug Administration (DGDA)
  • Bhutan – Drug Regulatory Authority
  • China* – CFDA/NMPA: State Food and Drug Administration
  • India – Central Drug Standards Control Organization (CDSCO)
  • Indonesia – POM (Pengawas Obat dan Makanan)
  • JAPAN* – PMDA: Ministry of Health, Labour and Welfare ~12%
  • Korea (South) – Korean Food and Drug Administration (KFDA) ~1%
  • Laos – Food and Drug Department
  • Malaysia – Ministry of Health (MOH)
  • Nepal – Department of Drug Administration
  • Philippines – Department of Health (DOH)
  • Singapore – Health Sciences Authority (HSA)
  • Sri Lanka – Ministry of Health (MOH)
  • Taiwan (Republic of China) – Taiwan Food and Drug Administration (TFDA)
  • Thailand – Food and Drug Administration of Thailand
  • Vietnam – Drug Administration of Vietnam
  • Algeria – Ministry of Health and Population
  • Botswana – Ministry of Health (MOH)
  • Burkina Faso – Le Ministère de la Santé
  • Ghana – Food and Drugs Authority
  • Kenya – Pharmacy and Poisons Board
  • Morocco – Ministry of Health
  • Nigeria – National Agency for Food and Drug Administration and Control
  • Rwanda – Ministry of Health
  • Senegal – Ministère de la Santé et de l’Action Sociale
  • South Africa – Medicines Control Council (MCC)
  • Swaziland – Ministry of Health
  • Tanzania – Tanzania Food and Drug Authority (TFDA)
  • Uganda – National Drug Authority

Local Pharmacovigilance Regulatory Bodies

  • Australia – Therapeutic Goods Administration (TGA)
  • New Zealand – MEDSAFE
  • North America
  • Canada – Health Canada ~2%
  • USA* – FDA: Food and Drug Administration ~33%
  • Central/South America
  • Argentina – ANMAT
  • Brazil – Agencia Nacional de Vigilancia Sanitaria (ANVISA)
  • Chile – Instituto de Salud Publico (ISP)
  • Columbia – Instituto Nacional de Vigilancia Medicamentos y Alimentos (INVIMA)
  • Costa Rica – Ministerio de Salud
  • Cuba – CECMED
  • Dominican Republic – Dirección General de Drogas y Farmacias
  • Jamaica – Ministry of Health
  • Mexico – Comisión Federal para la Protección contra Riesgos Sanitarios (COFEPRIS)
  • Paraguay – Ministro de Salud Pública y Bienestar Social
  • Peru – Ministerio de Salud
  • Uruguay – Ministerio de Salud Publica
  • European Union* – EMA: European Medicines Agency ~17%
  • Armenia – Scientific Centre of Drug and Medical Technology Expertise
  • Austria – Agency for Health and Food Safety (AGES)
  • Belgium – Federal Agency for Medicines and Health Products
  • Bulgaria – Bulgarian Drug Agency
  • Croatia – Agency for Medicinal Products and Medical Devices of Croatia
  • Cyprus – Ministry of Health
  • Czech Republic – State Institute for Drug Control
  • Denmark – Danish Medicines Agency
  • Estonia – State Agency of Medicines
  • Finland – Finish Medicines Agency
  • France – Agence Nationale de Sécurité du Medicament et des Produits de Santé
  • Germany – Federal Institute for Drugs and Medical Devices
  • Georgia – Regulation Agency for Medical and Pharmaceutical Activities
  • Greece – National Organisation for Medicines
  • Hungary – National Institute of Pharmacy
  • Iceland – Icelandic Medicines Agency
  • Ireland – Irish Medicines Board
  • Italy – National Institute of Health
  • Lithuania – State Medicines Control Agency
  • Luxembourg – Ministry of Health
  • Malta – Maltese Medicines AuthorityMoldova – Medicines Agency
  • Netherlands – Medicines Evaluation Board
  • Norway – Norwegian Medicines Agency
  • Poland – The Office for Registration of Medicinal Products, Medical Devices and Biocidal Products
  • Portugal – National Authority of Medicines and Health Products
  • Romania – National Medicines Agency
  • Russia – Ministry of Health of the Russian Federation

System Factors in Patient Safety

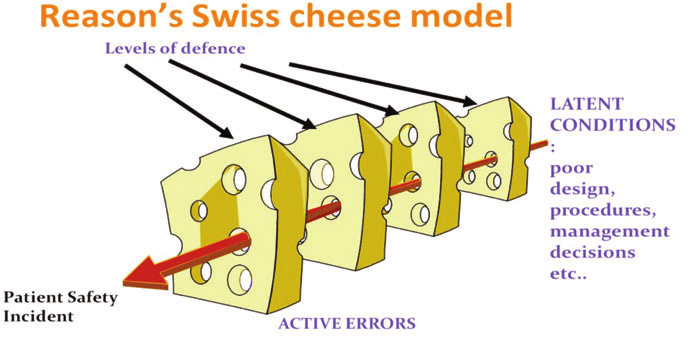
James Reason created the Swiss cheese model to explain how faults in different layers of a system lead to incidents. This model shows how a fault in one layer of a health care system of care is usually not enough to cause an accident. Adverse events usually occur when a number of faults occur in a number of layers (for example, fatigued workers plus inadequate procedures plus faulty equipment) and momentarily line up to permit a “trajectory” of accident opportunity.

Lets see the scenario of a medication error happening in a patient as an example:

He was having heartburn for quite a few days. Not able to take it much longer, Madhav visited the doctor. He explained his symptoms and the doctor wrote a simple prescription for heartburn but the writing was not clear.
Madhav did not clarify the medication name with the physician and took the prescription to the pharmacist.
The pharmacist deciphered the medication to the best of his understanding and dispensed the medication.

Madhav returned two days later with completely different symptoms in addition to continuing heartburn, a review revealed that the patient was dispensed aripiprazole, an antipsychotic instead of rabeprazole, an anti ulcer drug, and the symptoms the patient was experiencing now were the adverse reactions of the incorrect drug he was taking.

Now, who is at fault here, there were many barriers to this medication error – the doctor (if he gave computerized prescription or made sure the hand writing was clear), Patient (who could have confirmed the medication name with the physician), the pharmacist (who understood the concept of a sound alike drugs and made sure to confirm it with the physician). All the barriers missed the check points and the the holes of the swiss cheese model aligned for this error to happen.

Looking at it from systems approach, there are various factors involved – the issue of illegible hand written prescription, the lack of training of the pharmacist on sound alike drugs. Awareness at patient level.
So, when we go to the root of it, there is a need to review systems in healthcare that are error prone and change them. The first step towards doing root cause analysis is reporting errors. The major road block to reporting is the culture of blame and shame of an individual, which discourages individuals from reporting AEs or errors.

The National patient safety implementation framework calls for establishing an error and AE reporting system that is non-punitive, confidential, independent, timely, system oriented and responsive in nature.
The change is coming

#PhVFITpatientsafetycampaign

Human Factors in Patient Safety

To err is human, and this is why it is so important to apply human factors for patient safety, and develop procedures to minimize error.

How we apply human factors? Aviation industry applies the principles of human factors, and has built a controlled system of checklists and protocols to minimize the errors! The stakes are so high, you can not afford to err in avaiation, right.

Now just imagine how all the more important human factors are in a hospital environment. However, research has shown that human factors and ergonomics are often ignored in health care.

In a health care environment, there are a number of human factors involved that can lead to errors. To name a few, fatigue due to longer shifts, stress of emergencies, change of duties that can lead to communication issues during handovers, distractions during procedures, etc.

For e.g. a lab technician takes samples for a patient in a common ward, and soon after is called by another patient for some support, however, in the hurry, he misses labeling the samples and they get mixed up. If we understand this common human factor, it makes sense to develop a protocol to minimize the distractions.

Time outs in operation theatre before starting an operation is also an example of a protocol to minimize procedural errors.

The problem starts when the protocols are deviated from, example the surgeon feels he knows all details and does not need a time out.

Therefore, the protocols are not enough, adherence to them is most essential. A failure to apply human-factors principles is a key aspect of most adverse events (harm to patients) in health care.

The WHO’s curriculum guide for patient safety recommends: all health-care workers to have a basic understanding and training of human-factors principles, and according to this understanding the ergonomics of the health care facility should be customized to minimize error.

Let us take another example:

Here is an insightful article from Uppsala Monitoring Centre Uppsala reports that talks about the medication errors due to two component vaccines and the harm they could cause (link at the bottom).

What kind of errors?

The article shares a number of real life medication error examples that have happened in different countries across the world – and their impact.
Errors like:

The vaccine components do not mix properly or incorrect diluent was used to reconstitute a vaccine.

The Impact:

In 2014, 15 children in Syria died after atracurium (a paralysing agent) was used to reconstitute a measles vaccine. Apparently the ampule packaging of the drug was similar to the vaccine diluent packing and the mix-up occurred.

A similar incident in Samoa in 2018 not only led to the death of two infants but also impeded the immunisation efforts in the country, which in turn led to an outbreak of measles in the country that infected 4300 people and claimed 70 lives (majorly 5 year olds).

These were common human errors, but when you go the root of it, you find they could have been prevented.

The article further states, “human error can never be eliminated, however, many factors that contribute to the error can be identified and improved to minimize the chances of it occurring. International medication safety network (IMSN) has issued a position statement calling for greater worldwide attention to the problem of unsafe design of vaccine packaging and labeling”.

To err is human, but not to learn from errors and keep erring is not!

Read further under the link below. It is a must read, do not miss.

https://lnkd.in/dhKnwsQM